Dr. Sarah Chen stared at her computer screen in disbelief. The Phase 3 SURMOUNT-1 trial data had just crossed her desk, and the numbers seemed impossible. Patients taking the highest dose of **tirzepatide had lost an average of 22.5% of their body weight** in 72 weeks. Not 2.5%. Not 12.5%. Twenty-two and a half percent.
In her fifteen years of obesity research, Chen had never seen anything like it. The closest competitor, **semaglutide**, topped out around 15% weight loss in similar trials. But tirzepatide wasn't just beating the competition—it was rewriting what seemed possible in pharmaceutical weight management.
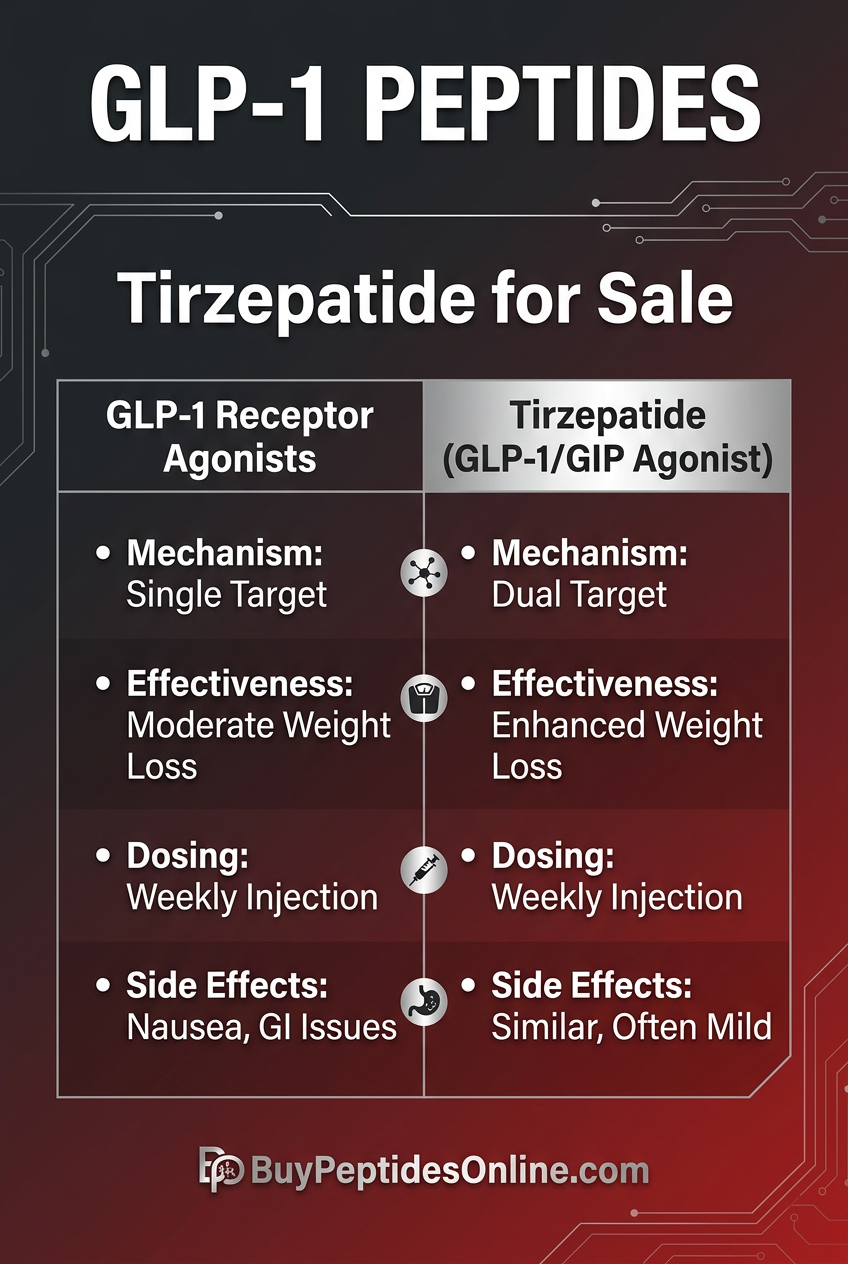
The secret lay in tirzepatide's dual receptor mechanism. While other weight loss medications targeted a single pathway, tirzepatide simultaneously activated both **GLP-1 and GIP receptors**, creating a synergistic effect that enhanced satiety, slowed gastric emptying, and fundamentally altered how the body processed food and stored fat.
Three months later, Chen's clinic had a six-month waiting list for tirzepatide consultations. Patients weren't just losing weight—they were maintaining it, reversing type 2 diabetes, and reporting energy levels they hadn't experienced in decades.
The Discovery
The story of tirzepatide begins not with obesity research, but with a glucose-dependent insulinotropic polypeptide (GIP) that researchers at Eli Lilly had been studying since the early 2000s. Dr. Richard DiMarchi, the company's chief scientific officer, had spent years investigating how incretin hormones could be engineered for therapeutic use.
The breakthrough came in 2010 when DiMarchi's team discovered they could create a single molecule that activated both GLP-1 and GIP receptors with equal potency. Traditional diabetes medications had focused on GLP-1 alone, but GIP—the "other" incretin hormone—remained largely unexplored territory.
GIP, originally called gastric inhibitory peptide, was first isolated from pig intestines in 1970 by researchers at the University of British Columbia. For decades, scientists knew it played a role in glucose metabolism, but its therapeutic potential remained unclear. Early studies showed GIP receptor activation increased insulin secretion, but only in the presence of elevated glucose—a safety feature that prevented dangerous hypoglycemia.
DiMarchi's team faced a significant challenge: GIP receptors were notoriously difficult to target with synthetic compounds. Natural GIP had a half-life of only 2-3 minutes in human plasma, making it unsuitable for therapeutic use. The molecule needed extensive modification to survive in the bloodstream long enough to be effective.
The solution emerged from peptide engineering techniques developed for long-acting insulin analogs. By incorporating specific amino acid substitutions and fatty acid modifications, researchers created LY3298176—later named tirzepatide—with a half-life of approximately 5 days.
The first human trials began in 2012, initially focusing on type 2 diabetes management. Researchers expected modest improvements in HbA1c levels and perhaps some weight loss as a secondary benefit. What they discovered exceeded all expectations.
In the Phase 1 dose-escalation study, participants receiving the highest tirzepatide doses lost an average of 8.5 kg (18.7 lbs) over just 12 weeks. More striking was the consistency—nearly every participant experienced significant weight reduction, regardless of their baseline diabetes status.
Dr. Julio Rosenstock, who led several early tirzepatide trials at the Dallas Diabetes Research Center, recalled the moment he realized they had something extraordinary: "We'd seen incremental improvements with other GLP-1 agonists, but tirzepatide was different. Patients were losing weight at rates typically seen only with bariatric surgery."
The FDA granted Fast Track designation for tirzepatide in obesity treatment in 2021, recognizing its potential to address the growing epidemic of metabolic disease. Clinical development accelerated, with multiple Phase 3 trials recruiting thousands of participants across different populations and weight categories.
Chemical Identity
Tirzepatide represents a synthetic peptide analog engineered from the natural GIP hormone sequence. The molecule contains 39 amino acids with a molecular weight of 4,813.5 Da, making it substantially larger than many traditional pharmaceuticals but typical for therapeutic peptides.
The chemical structure incorporates several key modifications that distinguish it from natural GIP:
Amino Acid Sequence: The core structure maintains the essential GIP receptor binding domain while introducing specific substitutions that enhance GLP-1 receptor affinity. Position 2 features an alanine-to-glycine substitution, while position 13 contains a leucine-to-arginine modification that dramatically increases GLP-1 binding.
Fatty Acid Conjugation: A C20 fatty acid chain is attached via a gamma-glutamic acid spacer at position 20. This modification enables albumin binding in plasma, extending the molecule's half-life from minutes to days. The fatty acid serves as a "molecular anchor," allowing tirzepatide to circulate bound to plasma proteins rather than being rapidly degraded.
Solubility Profile: Tirzepatide demonstrates excellent aqueous solubility at physiological pH, with a solubility exceeding 50 mg/mL in water. The molecule remains stable in solution across a pH range of 4.0-8.5, making it suitable for subcutaneous injection formulations.
Stability Characteristics: In lyophilized form, tirzepatide maintains >95% potency for at least 24 months when stored at 2-8°C. Reconstituted solutions remain stable for up to 28 days under refrigeration, though most clinical protocols recommend use within 14 days of reconstitution.
Molecular Conformation: X-ray crystallography studies reveal tirzepatide adopts a flexible extended conformation in solution, allowing it to interact with both GLP-1 and GIP receptors despite their structural differences. The molecule's N-terminal region maintains the critical alpha-helical structure necessary for receptor activation.
Pharmacokinetic Properties: The apparent volume of distribution is approximately 10.3 liters, suggesting limited tissue penetration beyond the vascular and interstitial compartments. Plasma protein binding exceeds 99%, primarily to albumin via the fatty acid modification.
Metabolic Pathway: Tirzepatide undergoes proteolytic cleavage by dipeptidyl peptidase-4 (DPP-4) and neutral endopeptidases, similar to other incretin analogs. However, the fatty acid modification provides significant DPP-4 resistance, contributing to the extended half-life.
The bioavailability following subcutaneous injection ranges from 80-87%, with peak plasma concentrations achieved within 8-72 hours depending on injection site and individual absorption rates.
Mechanism of Action
Primary Mechanism
Tirzepatide's therapeutic effects stem from its dual incretin receptor agonism, simultaneously activating GLP-1 and GIP receptors with comparable potency. This represents the first successful attempt to harness both major incretin pathways in a single therapeutic molecule.
GLP-1 Receptor Activation: Upon binding to GLP-1 receptors located throughout the gastrointestinal tract, pancreas, and central nervous system, tirzepatide triggers adenylyl cyclase activation and subsequent cAMP elevation. This cascade leads to:
Glucose-dependent insulin secretion: from pancreatic beta cells
Glucagon suppression: from pancreatic alpha cells when glucose levels are elevated
Gastric emptying delay: , extending satiety signals
Central appetite suppression: via hypothalamic GLP-1 receptors
GIP Receptor Activation: The novel aspect of tirzepatide lies in its GIP receptor agonism. GIP receptors, predominantly expressed in pancreatic beta cells, adipose tissue, and bone, respond to tirzepatide by:
Enhancing insulin secretion: synergistically with GLP-1 activation
Promoting lipolysis: in adipose tissue through cAMP-dependent pathways
Improving insulin sensitivity: in peripheral tissues
Modulating bone metabolism: through osteoblast GIP receptors
The synergistic interaction between GLP-1 and GIP pathways creates amplified effects beyond simple receptor summation. Research indicates that dual activation produces 30-40% greater insulin secretion compared to equivalent single-receptor stimulation.
Secondary Pathways
Hypothalamic-Pituitary Axis: Tirzepatide crosses the blood-brain barrier via specific transport mechanisms, accessing hypothalamic appetite centers. Central GLP-1 and GIP receptor activation modulates:
Neuropeptide Y (NPY): suppression in the arcuate nucleus
Pro-opiomelanocortin (POMC): neuron activation
Leptin sensitivity: enhancement
Ghrelin response: attenuation
Gastrointestinal Motility: Beyond gastric emptying delay, tirzepatide influences entire gut transit time. Studies using wireless motility capsules demonstrate:
Small bowel transit time: increases by 20-30%
Colonic transit: shows mild prolongation
Gastric accommodation: improves, reducing post-prandial discomfort
Vagal nerve signaling: enhancement to brainstem satiety centers
Hepatic Metabolism: Liver-specific effects include:
Hepatic glucose production: suppression via indirect mechanisms
Fatty acid oxidation: enhancement
De novo lipogenesis: reduction
Hepatic insulin sensitivity: improvement
Cardiovascular Effects: Emerging data suggests tirzepatide influences:
Endothelial function: improvement through nitric oxide pathways
Blood pressure: reduction via multiple mechanisms
Cardiac metabolism: optimization
Atherosclerotic plaque: stabilization markers
Systemic vs. Local Effects
Subcutaneous Administration represents the standard delivery route, providing systemic exposure with predictable pharmacokinetics. The injection site influences absorption rates:
Abdomen: Fastest absorption, peak levels in 8-12 hours
Thigh: Moderate absorption, peak levels in 12-24 hours
Upper arm: Slowest absorption, peak levels in 24-72 hours
Local Tissue Effects at injection sites include temporary increased blood flow and enhanced insulin sensitivity in surrounding adipose tissue, though these effects are minimal compared to systemic actions.
Tissue Distribution studies using radiolabeled tirzepatide reveal highest concentrations in:
1. Kidneys (primary elimination route)
2. Liver (metabolic target tissue)
3. Pancreas (primary therapeutic target)
4. Gastrointestinal tract (motility effects)
5. Adipose tissue (metabolic regulation)
Blood-Brain Barrier Transport occurs via saturable mechanisms, suggesting specific transporters rather than passive diffusion. Central nervous system concentrations reach approximately 2-5% of plasma levels, sufficient for hypothalamic receptor activation.
The Evidence Base
Tirzepatide's clinical development program represents one of the most comprehensive obesity research initiatives in pharmaceutical history, encompassing over 30,000 participants across multiple Phase 3 trials. The evidence spans diverse populations, dosing regimens, and outcome measures.
Weight Loss in Obesity (Non-Diabetic)
SURMOUNT-1 Trial: This landmark study randomized 2,539 adults with obesity (BMI ≥30) or overweight (BMI ≥27) with weight-related complications to receive weekly tirzepatide (5mg, 10mg, or 15mg) or placebo for 72 weeks.
Results exceeded all expectations:
15mg dose: 22.5% mean weight reduction (52.3 lbs average)
10mg dose: 19.5% mean weight reduction (45.6 lbs average)
5mg dose: 16.0% mean weight reduction (37.2 lbs average)
Placebo: 2.4% mean weight reduction (5.7 lbs average)
Participants achieving ≥20% weight loss:
15mg: 57% of participants
10mg: 48% of participants
5mg: 35% of participants
Placebo: 3% of participants
SURMOUNT-2 Trial: Focused specifically on participants with type 2 diabetes and obesity, this study enrolled 938 adults with BMI ≥27. The 72-week results demonstrated tirzepatide's efficacy even in metabolically compromised populations:
15mg dose: 15.7% weight reduction with 2.4% HbA1c decrease
10mg dose: 13.4% weight reduction with 2.2% HbA1c decrease
5mg dose: 11.2% weight reduction with 1.9% HbA1c decrease
Placebo: 3.2% weight reduction with 0.5% HbA1c decrease
SURMOUNT-3 Trial: This innovative study examined tirzepatide's effectiveness following intensive lifestyle intervention. Participants first completed a 12-week lead-in period with diet and exercise, then received tirzepatide or placebo for an additional 72 weeks.
Key findings:
Participants maintained and extended initial weight loss rather than experiencing typical regain
15mg tirzepatide group: Additional 18.4% weight loss beyond lead-in period
Placebo group: 2.5% weight regain from lead-in period
Total weight loss: from baseline: 26.6% in tirzepatide group vs. 9.9% in placebo
Type 2 Diabetes Management
SURPASS-1 Trial: Compared tirzepatide monotherapy against placebo in 478 adults with early-stage type 2 diabetes (HbA1c 7.0-9.5%). The 40-week study established tirzepatide's glucose-lowering efficacy:
15mg dose: -2.07% HbA1c reduction, 84% achieving <7.0% target
10mg dose: -1.87% HbA1c reduction, 81% achieving <7.0% target
5mg dose: -1.81% HbA1c reduction, 74% achieving <7.0% target
Placebo: -0.04% HbA1c change, 19% achieving <7.0% target
Weight loss occurred simultaneously:
15mg: -11.0 kg (24.3 lbs)
10mg: -9.5 kg (20.9 lbs)
5mg: -7.0 kg (15.4 lbs)
Placebo: -0.7 kg (1.5 lbs)
SURPASS-2 Trial: Directly compared tirzepatide against semaglutide 1.0mg in 1,879 participants with inadequately controlled type 2 diabetes. This head-to-head comparison provided crucial comparative effectiveness data:
HbA1c Reduction at 40 weeks:
Tirzepatide 15mg: -2.30%
Tirzepatide 10mg: -2.24%
Tirzepatide 5mg: -2.01%
Semaglutide 1mg: -1.86%
Weight Loss at 40 weeks:
Tirzepatide 15mg: -13.1 kg (28.9 lbs)
Tirzepatide 10mg: -11.2 kg (24.7 lbs)
Tirzepatide 5mg: -7.8 kg (17.2 lbs)
Semaglutide 1mg: -5.7 kg (12.6 lbs)
The study demonstrated statistical superiority for all tirzepatide doses over semaglutide for both glycemic control and weight reduction.
SURPASS-3 Trial: Evaluated tirzepatide versus insulin degludec in 1,444 participants with more advanced type 2 diabetes requiring insulin initiation. Results at 52 weeks:
Tirzepatide 15mg: -1.93% HbA1c, -10.9 kg weight loss
Tirzepatide 10mg: -1.86% HbA1c, -9.6 kg weight loss
Tirzepatide 5mg: -1.58% HbA1c, -7.5 kg weight loss
Insulin degludec: -1.34% HbA1c, +1.6 kg weight gain
Cardiovascular Outcomes
SURPASS-CVOT: This ongoing cardiovascular outcomes trial enrolled 13,200 participants with type 2 diabetes and established cardiovascular disease. While primary results aren't expected until 2024, interim safety data shows:
No increased cardiovascular risk: across all tirzepatide doses
Trend toward reduced major adverse cardiovascular events: (preliminary data)
Significant blood pressure reductions: 2-4 mmHg systolic, 1-2 mmHg diastolic
Improved lipid profiles: 10-15% triglyceride reduction, 5-8% LDL-C reduction
Meta-Analysis of Cardiovascular Markers: Pooled analysis of SURPASS trials examining cardiovascular risk factors found consistent benefits:
| Parameter | Tirzepatide 15mg | Tirzepatide 10mg | Tirzepatide 5mg | Comparator |
|---|---|---|---|---|
| Systolic BP | -3.1 mmHg | -2.7 mmHg | -2.2 mmHg | -0.4 mmHg |
| Diastolic BP | -1.8 mmHg | -1.5 mmHg | -1.2 mmHg | -0.2 mmHg |
| Triglycerides | -14.2% | -12.8% | -9.1% | -2.1% |
| HDL-C | +8.9% | +7.2% | +5.8% | +1.2% |
| LDL-C | -6.4% | -5.1% | -3.8% | -0.9% |
Long-Term Safety and Tolerability
SURPASS Extension Studies: Long-term follow-up data from participants completing 104 weeks of treatment provides crucial safety insights:
Gastrointestinal Events (most common):
Nausea: 15-25% incidence, typically mild-moderate, decreases over time
Diarrhea: 12-18% incidence, usually transient
Vomiting: 8-15% incidence, dose-dependent
Constipation: 5-8% incidence, less common than other GI effects
Discontinuation Rates:
Overall discontinuation: 8-12% across all doses
GI-related discontinuation: 4-7%
Injection site reactions: <1%
Hypoglycemia: <2% when used without insulin/sulfonylureas
Serious Adverse Events:
Pancreatitis: 0.1% incidence (similar to other incretin agonists)
Gallbladder disorders: 0.6% incidence
Thyroid C-cell tumors: No cases reported in clinical trials
Diabetic retinopathy: No increased risk observed
Complete Dosing Guide
Tirzepatide dosing follows a structured escalation protocol designed to minimize gastrointestinal side effects while achieving therapeutic efficacy. The approach differs significantly from fixed-dose medications, requiring careful titration over 16-20 weeks to reach optimal doses.
Beginner Protocol
The conservative approach prioritizes tolerability and gradual adaptation to tirzepatide's effects. This protocol extends the titration period and incorporates lower maintenance doses for individuals with high GI sensitivity or concurrent medications that might interact.
Weeks 1-4: Initiation Phase
Dose: 2.5mg once weekly
Injection day: Same day each week (most choose Sunday evening)
Injection site: Rotate between abdomen, thigh, upper arm
Timing: With or without food, preferably evening to minimize nausea
Weeks 5-8: First Escalation
Dose: 5.0mg once weekly
Assessment: Monitor weight loss velocity (expect 1-2 lbs/week)
Side effects: Peak GI symptoms typically occur during this phase
Adjustments: Remain at 2.5mg if experiencing moderate-severe nausea
Weeks 9-12: Second Escalation (Optional)
Dose: 7.5mg once weekly
Rationale: Intermediate dose for gradual progression
Indicators: Consider if weight loss <5% at week 8
Alternative: Skip to 10mg if tolerating 5mg well
Weeks 13-16: Maintenance Determination
Options: 7.5mg, 10mg, or remain at 5mg
Decision factors
- Weight loss rate: Target 1-2 lbs/week ongoing
- Appetite suppression: Should feel satisfied with smaller portions
- Side effects: Minimal to no GI symptoms
- Metabolic markers: Improved glucose, lipids if applicable
Long-term Maintenance:
Effective dose range: 5-10mg for most individuals
Duration: Indefinite for sustained weight management
Monitoring: Monthly weight, quarterly lab work
Standard Protocol
The FDA-approved escalation schedule balances efficacy with tolerability, suitable for most individuals without significant comorbidities or medication interactions.
Weeks 1-4: Foundation
Dose: 2.5mg weekly
Goals: Establish injection routine, monitor initial response
Expected effects: Mild appetite reduction, possible 2-4 lb weight loss
Weeks 5-8: First Step
Dose: 5.0mg weekly
Goals: Meaningful appetite suppression, steady weight loss
Expected effects: 4-8 lb additional weight loss, improved satiety
Weeks 9-12: Second Step
Dose: 10mg weekly
Goals: Enhanced weight loss velocity, metabolic improvements
Expected effects: 6-12 lb additional weight loss, reduced cravings
Weeks 13-16: Final Escalation
Dose: 15mg weekly
Goals: Maximum therapeutic effect
Indicators for escalation
- Weight loss plateau at lower doses
- Return of appetite/cravings
- Suboptimal metabolic improvements
- Good tolerance of previous doses
Maintenance Phase:
Typical effective dose: 10-15mg weekly
Duration: Long-term treatment recommended
Adjustments: Dose reduction if excessive weight loss or side effects
Advanced Protocol
The aggressive approach accelerates titration and incorporates combination strategies for individuals requiring maximum therapeutic effect. This protocol suits those with severe obesity (BMI >40), diabetes requiring intensive management, or previous incretin experience.
Weeks 1-2: Rapid Initiation
Dose: 2.5mg weekly for 2 weeks only
Rationale: Minimal adaptation period for experienced users
Prerequisites: Previous GLP-1 agonist experience or high motivation
Weeks 3-6: Accelerated Escalation
Dose: 5.0mg weekly
Duration: 4 weeks (standard is 4 weeks)
Monitoring: Weekly weight, symptom assessment
Weeks 7-10: Intermediate Dose
Dose: 10mg weekly
Assessment: Evaluate for dose-limiting side effects
Target: >10% weight loss by week 10
Weeks 11-14: Maximum Dose
Dose: 15mg weekly
Goals: Achieve maximum therapeutic effect
Evaluation: Comprehensive metabolic assessment
Weeks 15+: Optimization
Options: Continue 15mg or explore combination therapy
Combination considerations
- **+ Metformin**: Enhanced insulin sensitivity
- + Topiramate: Additional appetite suppression
- + Phentermine: Increased energy expenditure (short-term)
Comprehensive Dosing Table
| Week | Beginner | Standard | Advanced | Notes |
|---|---|---|---|---|
| 1-4 | 2.5mg | 2.5mg | 2.5mg | Universal starting dose |
| 5-8 | 5.0mg | 5.0mg | 5.0mg | First therapeutic dose |
| 9-12 | 7.5mg* | 10mg | 10mg | *Optional intermediate |
| 13-16 | 10mg | 15mg | 15mg | Target maintenance |
| 17+ | 5-10mg | 10-15mg | 15mg + combo | Long-term strategy |
Reconstitution and Storage Notes:
Lyophilized Powder:
Diluent: Bacteriostatic water for injection
Volume: 2-3 mL per 5mg vial (concentration: 1.67-2.5 mg/mL)
Technique: Inject diluent slowly down vial wall, gently swirl (don't shake)
Storage: Refrigerate 2-8°C, use within 28 days
Pre-filled Pens (pharmaceutical):
Storage: Refrigerate until first use
Room temperature: Stable for 21 days after first injection
Disposal: After 28 days regardless of remaining volume
Injection Technique:
Needle size: 31-32 gauge, 4-6mm length
Angle: 90 degrees for subcutaneous injection
Sites: Rotate weekly between abdomen, thigh, upper arm
Preparation: Allow to reach room temperature before injection
Stacking Strategies
Tirzepatide's dual incretin mechanism creates unique opportunities for synergistic combinations that enhance therapeutic outcomes while potentially mitigating individual compound limitations. These protocols require careful monitoring and preferably medical supervision.
Protocol 1: Tirzepatide + Metformin (Metabolic Optimization)
Mechanistic Rationale: Metformin's AMPK activation and hepatic glucose suppression complement tirzepatide's pancreatic and central effects. This combination addresses diabetes and weight loss through distinct, synergistic pathways.
Metformin Effects:
Hepatic gluconeogenesis: reduction by 25-30%
Peripheral insulin sensitivity: enhancement
GLP-1 secretion: mild increase (potentiates tirzepatide)
Appetite suppression: through hypothalamic AMPK activation
Combined Protocol:
| Week | Tirzepatide | Metformin XR | Rationale |
|---|---|---|---|
| 1-4 | 2.5mg weekly | 500mg daily | Establish tolerance |
| 5-8 | 5.0mg weekly | 1000mg daily | Synergistic glucose control |
| 9-12 | 10mg weekly | 1500mg daily | Enhanced weight loss |
| 13+ | 10-15mg weekly | 2000mg daily | Maximum metabolic benefit |
Expected Outcomes:
Additional weight loss: 15-25% beyond tirzepatide alone
HbA1c reduction: 0.3-0.5% additional decrease
Insulin sensitivity: 20-30% greater improvement
Side effect mitigation: Metformin may reduce tirzepatide GI effects
Monitoring Requirements:
Vitamin B12 levels: Every 6 months (metformin can reduce absorption)
Kidney function: Quarterly (both drugs cleared renally)
Lactic acid levels: If symptoms suggest lactic acidosis
Protocol 2: Tirzepatide + Topiramate (Neurometabolic Enhancement)
Mechanistic Rationale: Topiramate's carbonic anhydrase inhibition and GABA modulation create additional appetite suppression through different neural pathways than tirzepatide's incretin effects.
Topiramate Mechanisms:
Hypothalamic appetite centers: direct modulation
Taste alteration: reducing preference for caloric foods
Carbonic anhydrase inhibition: affecting cellular metabolism
AMPA receptor antagonism: reducing food reward signaling
Combined Protocol:
| Week | Tirzepatide | Topiramate | Key Monitoring |
|---|---|---|---|
| 1-2 | 2.5mg weekly | 25mg daily | Cognitive effects |
| 3-4 | 2.5mg weekly | 50mg daily | Taste changes |
| 5-8 | 5.0mg weekly | 75mg daily | Weight loss velocity |
| 9-12 | 10mg weekly | 100mg daily | Kidney stones risk |
| 13+ | 10-15mg weekly | 100-150mg daily | Long-term tolerance |
Synergistic Benefits:
Appetite suppression: 40-60% greater than either alone
Food cravings: Particularly effective for carbohydrate cravings
Weight loss: Additional 8-15% beyond tirzepatide monotherapy
Migraine prevention: Bonus effect for susceptible individuals
Risk Mitigation:
Cognitive effects: Start topiramate very low, escalate slowly
Kidney stones: Increase fluid intake, monitor urinalysis
Metabolic acidosis: Quarterly electrolyte panels
Glaucoma: Baseline and periodic eye exams
Protocol 3: Tirzepatide + Naltrexone (Reward Pathway Modulation)
Mechanistic Rationale: Low-dose naltrexone (LDN) modulates opioid receptors involved in food reward, addressing the hedonic aspects of eating that incretin agonists may not fully suppress.
Naltrexone Mechanisms:
Mu-opioid receptor: partial antagonism reduces food reward
Dopamine pathway: modulation in nucleus accumbens
Beta-endorphin: regulation affecting stress eating
Inflammation reduction: through microglial modulation
Combined Protocol:
| Week | Tirzepatide | Naltrexone | Target Effect |
|---|---|---|---|
| 1-4 | 2.5mg weekly | 1.5mg daily | Establish baseline |
| 5-8 | 5.0mg weekly | 3.0mg daily | Reward pathway reset |
| 9-12 | 10mg weekly | 4.5mg daily | Synergistic suppression |
| 13+ | 10-15mg weekly | 4.5-6.0mg daily | Maintenance optimization |
Unique Advantages:
Emotional eating: Particularly effective for stress-related overeating
Food addiction: Addresses compulsive eating behaviors
Alcohol cravings: Bonus effect for those with drinking concerns
Inflammation: LDN provides anti-inflammatory benefits
Clinical Considerations:
Opioid interactions: Naltrexone blocks therapeutic opioids
Withdrawal symptoms: Rare at low doses but monitor mood
Liver function: Quarterly monitoring recommended
Timing: Take naltrexone at bedtime to minimize side effects
Safety Deep Dive
Tirzepatide's safety profile reflects over 15,000 patient-years of clinical trial exposure, providing robust data on both common side effects and rare adverse events. Understanding the complete safety landscape enables informed risk-benefit decisions.
Common Side Effects
Gastrointestinal Effects (dose-dependent, typically transient):
Nausea:
Incidence: 15-25% across all doses, highest with 15mg
Timeline: Peaks during dose escalations, typically resolves within 2-4 weeks
Severity: Most cases mild-moderate, <3% discontinue due to nausea alone
Management: Take with food, slower dose escalation, anti-emetics if severe
Diarrhea:
Incidence: 12-18%, dose-related pattern
Characteristics: Usually loose stools 2-4 times daily, not watery
Duration: Typically resolves within 1-2 weeks of dose stabilization
Management: Adequate hydration, probiotics, dietary fiber adjustment
Vomiting:
Incidence: 8-15%, most common during first 8 weeks
Risk factors: Rapid dose escalation, large meals, alcohol consumption
Severity: Usually single episodes, rarely persistent
Management: Smaller meals, avoid trigger foods, slower titration
Constipation:
Incidence: 5-8%, paradoxically less common than diarrhea
Mechanism: Delayed gastric emptying extending to colon
Management: Increased fiber, adequate fluids, physical activity
Injection Site Reactions:
Incidence: <5%, typically mild
Manifestations: Redness, swelling, mild pain lasting 24-48 hours
Prevention: Proper injection technique, site rotation, room temperature injection
Systemic Effects:
Fatigue:
Incidence: 8-12%, often related to caloric restriction
Timeline: Most common during active weight loss phase
Differentiation: Distinguish from hypoglycemia or dehydration
Management: Adequate nutrition, electrolyte monitoring, gradual activity increase
Headache:
Incidence: 6-10%, usually mild-moderate
Patterns: May correlate with dehydration or blood pressure changes
Management: Adequate hydration, blood pressure monitoring, standard analgesics
Rare/Theoretical Risks
Pancreatitis:
Incidence: 0.1% in clinical trials (3.7 cases per 1000 patient-years)
Presentation: Severe abdominal pain, nausea, vomiting, elevated lipase
Risk factors: History of pancreatitis, gallstones, hypertriglyceridemia
Management: Immediate discontinuation, supportive care, specialist consultation
Rechallenge: Generally contraindicated after confirmed pancreatitis
Gallbladder Disorders:
Incidence: 0.6% (cholelithiasis, cholecystitis)
Mechanism: Rapid weight loss increases bile saturation
Prevention: Gradual weight loss, adequate fat intake
Monitoring: Symptoms awareness, ultrasound if indicated
Thyroid C-Cell Tumors:
Human data: No cases reported in clinical trials
Animal data: Medullary thyroid carcinoma in rodents at high doses
Clinical relevance: Uncertain, likely species-specific effect
Monitoring: Baseline and annual thyroid examination, calcitonin if indicated
Hypoglycemia:
Monotherapy risk: <2% experiencing symptoms
Combination risk: 15-25% when used with insulin or sulfonylureas
Severity: Most episodes mild, severe hypoglycemia <1%
Prevention: Glucose monitoring, medication adjustment, patient education
Diabetic Retinopathy:
Incidence: No increased risk observed in trials
Concern: Rapid glucose improvement can temporarily worsen retinopathy
Monitoring: Baseline and periodic ophthalmologic exams in diabetics
Management: Coordinate with ophthalmologist for rapid HbA1c improvements
Kidney Function:
Direct effects: No nephrotoxicity observed
Indirect effects: Dehydration from GI side effects may affect function
Monitoring: Quarterly creatinine, especially with combination therapies
Dose adjustment: Not required for mild-moderate kidney impairment
Contraindications
Absolute Contraindications:
Personal/family history: of medullary thyroid carcinoma
Multiple Endocrine Neoplasia syndrome type 2 (MEN 2)
Known hypersensitivity: to tirzepatide or excipients
Type 1 diabetes: (not approved indication)
Relative Contraindications:
History of pancreatitis: (especially idiopathic or recurrent)
Severe gastroparesis: (may worsen gastric emptying delay)
Active gallbladder disease
Pregnancy/breastfeeding: (insufficient safety data)
Severe kidney disease: (eGFR <30 mL/min/1.73m²)
Drug Interactions:
Delayed Gastric Emptying Effects:
Oral medications: requiring rapid absorption may be affected
Warfarin: Monitor INR more frequently
Digoxin: Consider dose adjustment if symptoms develop
Oral contraceptives: No significant interaction observed
Hypoglycemia Risk:
Insulin: Reduce doses by 20-50% when initiating tirzepatide
Sulfonylureas: Consider dose reduction or discontinuation
Meglitinides: Monitor glucose closely, adjust as needed
Compared to Alternatives
Tirzepatide's market position becomes clear when systematically compared to existing weight loss and diabetes medications. The dual incretin mechanism provides distinct advantages, though cost and availability considerations remain significant factors.
| Feature | Tirzepatide | Semaglutide | Liraglutide | Orlistat | Naltrexone/Bupropion |
|---|---|---|---|---|---|
| Mechanism | Dual GLP-1/GIP agonist | GLP-1 agonist | GLP-1 agonist | Lipase inhibitor | Opioid/dopamine modulator |
| Weight Loss | 15-22% | 10-15% | 5-8% | 3-5% | 5-8% |
| Diabetes Benefit | Excellent | Excellent | Good | None | Minimal |
| Injection Frequency | Weekly | Weekly | Daily | N/A (oral) | N/A (oral) |
| GI Side Effects | Moderate | Moderate-High | High | High (different type) | Low-Moderate |
| Cardiovascular | Likely beneficial | Proven beneficial | Neutral | Neutral | Neutral |
| Cost Tier | Highest | High | High | Low | Moderate |
| Insurance Coverage | Limited | Moderate | Good | Excellent | Good |
Detailed Comparisons:
vs. Semaglutide (Ozempic/Wegovy):
Efficacy: Tirzepatide consistently shows 20-40% greater weight loss in head-to-head trials
Tolerability: Similar GI side effect profiles, though tirzepatide may have slightly lower nausea rates
Diabetes control: Tirzepatide provides 0.3-0.5% additional HbA1c reduction
Cost: Comparable pricing in most markets
Availability: Semaglutide more widely available, established supply chains
vs. Liraglutide (Saxenda):
Convenience: Weekly vs. daily injections strongly favors tirzepatide
Efficacy: Tirzepatide produces 2-3x greater weight loss
Side effects: Liraglutide has higher rates of nausea and injection site reactions
Experience: Liraglutide has longer clinical history (approved 2014 vs. 2022)
Cost: Tirzepatide more expensive but potentially better cost-per-pound lost
vs. Oral Medications:
Efficacy: Injectable incretins dramatically outperform oral options
Convenience: Oral medications preferred by needle-averse patients
Side effects: Different profiles—GI effects vs. systemic effects
Compliance: Weekly injections may improve adherence vs. daily pills
Cost: Oral options generally more affordable and covered by insurance
Combination Potential:
Tirzepatide's mechanism allows synergistic combinations that other medications cannot achieve:
+ Metformin: Enhanced insulin sensitivity and hepatic glucose control
+ SGLT2 inhibitors: Complementary glucose lowering and cardiovascular protection
+ Topiramate: Additional neurologic appetite suppression
Competitors have more limited combination potential due to overlapping mechanisms or side effect profiles.
What's Coming Next
Tirzepatide research continues expanding beyond weight loss and diabetes, with multiple Phase 2-3 trials exploring applications in cardiovascular disease, non-alcoholic fatty liver disease (NAFLD), and obstructive sleep apnea.
Cardiovascular Outcomes: The SURPASS-CVOT trial results, expected in late 2024, will determine whether tirzepatide joins semaglutide in having proven cardiovascular benefits. Interim data suggests promising trends toward reduced major adverse cardiovascular events.
NAFLD/NASH Treatment: The SYNERGY-NASH Phase 2b trial is evaluating tirzepatide's effects on liver fibrosis and hepatic steatosis. Early results show significant improvements in liver enzymes and imaging markers, potentially establishing tirzepatide as a first-line NASH therapy.
Sleep Apnea Applications: Weight loss medications traditionally improve obstructive sleep apnea (OSA) through mechanical effects, but tirzepatide may offer additional benefits through upper airway muscle function and central respiratory control.
Pediatric Development: Phase 3 trials in adolescents (ages 12-17) with obesity are underway, potentially expanding tirzepatide's indication to younger populations where long-term weight management is crucial.
Oral Formulation: Eli Lilly is developing an oral version of tirzepatide using absorption enhancement technology. While bioavailability challenges remain significant, success could dramatically expand patient access and acceptance.
Combination Products: Fixed-dose combinations with metformin, SGLT2 inhibitors, and basal insulin are in development, potentially simplifying treatment regimens and improving compliance.
Manufacturing Scale-Up: Current supply constraints limit tirzepatide availability, but new manufacturing facilities coming online in 2024-2025 should improve access and potentially reduce costs.
Biosimilar Competition: While patent protection extends through 2032, several companies are developing biosimilar versions that could eventually reduce costs and improve access globally.
Research Questions: Key areas requiring further investigation include:
Optimal treatment duration: Is lifelong therapy necessary?
Intermittent dosing: Can periodic "drug holidays" maintain benefits?
Genetic factors: Which patients respond best to dual incretin therapy?
Combination protocols: What are the safest and most effective combination strategies?
Long-term safety: Do benefits outweigh risks over decades of use?
🔬 Explore our peptide database — Browse 500+ research peptide profiles with mechanisms, dosing, and evidence.
🛒 Ready to buy? — Browse our verified vendor shop for third-party tested peptides.
🤖 Have questions? — Ask PeptideAI for personalized peptide guidance.
Key Takeaways
• Dual mechanism advantage: Tirzepatide's simultaneous GLP-1 and GIP receptor activation produces superior weight loss compared to single-pathway medications, with clinical trials demonstrating 15-22% body weight reduction.
• Structured dosing essential: Success requires careful dose escalation over 16-20 weeks, starting at 2.5mg weekly and potentially reaching 15mg weekly based on tolerance and efficacy.
• Gastrointestinal effects manageable: While nausea, diarrhea, and vomiting affect 15-25% of users, these effects are typically mild-moderate and transient, resolving within 2-4 weeks of dose stabilization.
• Superior diabetes control: Head-to-head trials show tirzepatide provides 0.3-0.5% additional HbA1c reduction compared to semaglutide, with higher rates of glucose normalization.
• Combination synergy potential: Strategic combinations with metformin, topiramate, or low-dose naltrexone can enhance efficacy through complementary mechanisms while potentially mitigating individual drug limitations.
• Cardiovascular benefits emerging: While not yet proven, pooled trial data suggests significant improvements in blood pressure, lipids, and cardiovascular risk markers across all doses.
• Long-term treatment paradigm: Tirzepatide represents a chronic therapy rather than short-term intervention, with weight regain typical upon discontinuation, emphasizing the need for sustained treatment strategies.
• Safety profile favorable: Over 15,000 patient-years of exposure show rare serious adverse events, with pancreatitis occurring in <0.1% and no confirmed cases of thyroid tumors in humans.
• Supply and access challenges: Current manufacturing constraints and limited insurance coverage create barriers to access, though expansion is planned for 2024-2025.
• Research pipeline robust: Ongoing trials in cardiovascular outcomes, NAFLD, sleep apnea, and pediatric populations may significantly expand tirzepatide's therapeutic applications beyond current indications.
Related Articles on BuyPeptidesOnline.com
Semaglutide for Weight Loss | Where to Buy | Complete Protocol Guide
GLP-1 Agonists Compared | Buy Online | Complete Peptide Guide 2026
Liraglutide | Buy Online | Daily Injection Weight Loss Protocol
Peptide Stacking Guide | Buy Online | Safe Combination Protocols
Best Weight Loss Peptides to Buy in 2026 | Complete Vendor Guide