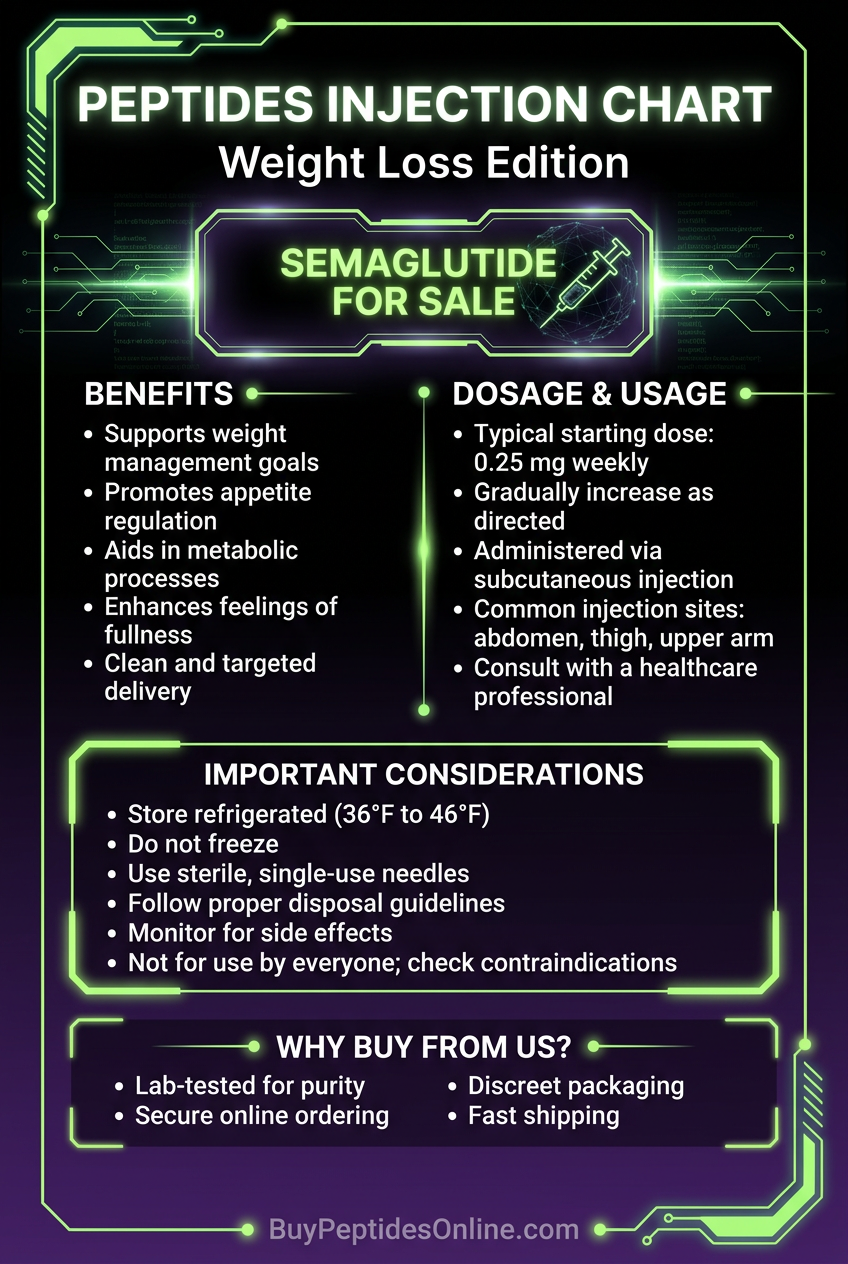
Sarah's scale hadn't budged in eighteen months. Despite calorie counting, intermittent fasting, and gym sessions that left her exhausted, the 42-year-old marketing executive remained stuck at 195 pounds. Then her endocrinologist mentioned a diabetes medication that was creating headlines for something entirely different: unprecedented weight loss.
Within six months of starting **semaglutide, Sarah had dropped 34 pounds. Her food cravings vanished. The constant mental chatter about her next meal simply... stopped. She wasn't alone. Clinical trials show semaglutide produces 15-20% weight loss** in non-diabetic adults — results that rival bariatric surgery without the scalpel.
But here's what Sarah's doctor didn't tell her: pharmaceutical semaglutide costs $1,300+ monthly without insurance. Meanwhile, research-grade semaglutide offers identical molecular structure at a fraction of the cost — lab-certified semaglutide is available from verified research suppliers, making this breakthrough accessible to researchers worldwide.
The Discovery
Semaglutide emerged from Novo Nordisk's laboratories in 2012, but its story begins decades earlier with a fascinating biological discovery. In 1982, researchers studying the Gila monster — a venomous lizard native to the American Southwest — isolated a hormone called **exendin-4** from its saliva — researchers can explore third-party tested Exendin-4 from trusted suppliers.
This lizard hormone had an unusual property: it could regulate blood sugar for extended periods. The Gila monster feeds infrequently, sometimes going months between meals, yet maintains stable glucose levels. Exendin-4 was the key.
Scientists recognized that exendin-4 mimicked **GLP-1 (glucagon-like peptide-1), a hormone humans produce in their intestines after eating. But there was a problem: natural GLP-1 degrades within minutes, destroyed by an enzyme called DPP-4**. The lizard version lasted much longer.
Novo Nordisk's team, led by Dr. Lotte Bjerre Knudsen, began engineering synthetic versions of GLP-1 that could resist DPP-4 breakdown. They tested hundreds of modifications, adjusting amino acid sequences and adding protective groups.
Their breakthrough came with semaglutide — a GLP-1 analog with a fatty acid side chain that allows it to bind to albumin proteins in blood. This binding creates a "depot effect," slowly releasing active hormone over days rather than minutes. The result: once-weekly injections instead of multiple daily doses.
Early trials focused on type 2 diabetes. Semaglutide reduced HbA1c by 1.5-2.0% and showed impressive cardiovascular benefits. But researchers noticed something unexpected: patients were losing substantial weight, even those without diabetes.
This observation launched the STEP trials — a series of studies specifically examining semaglutide for weight management. The results were unprecedented. In STEP 1, adults without diabetes lost an average of 14.9% of their body weight over 68 weeks. Some participants lost over 20%.
The FDA approved semaglutide for weight management as Wegovy in 2021, creating a new category of obesity medicine. Demand exploded. Supply shortages followed. Prices soared.
Today, research-grade semaglutide provides scientists and self-experimenters access to this revolutionary compound at accessible prices, fueling continued research into its mechanisms and applications. Those looking to compare semaglutide pricing from verified vendors will find research-grade options widely accessible today.
Chemical Identity
Semaglutide belongs to the incretin mimetic class of peptides, specifically engineered as a long-acting GLP-1 receptor agonist. Its molecular formula is C₁₈₇H₂₉₁N₄₅O₅₉, with a molecular weight of 4,113.58 daltons.
The peptide consists of 31 amino acids arranged in a specific sequence that closely mimics human GLP-1 but with crucial modifications. The backbone follows the natural GLP-1 structure with two key changes:
Position 8: Alanine replaces the natural amino acid, creating resistance to DPP-4 enzyme degradation.
Position 26: A fatty acid side chain (octadecanoic acid) attaches via a spacer and linker, enabling albumin binding.
This fatty acid modification is semaglutide's defining feature. The 18-carbon chain allows the peptide to reversibly bind to albumin proteins in blood and tissues. Approximately 99% of circulating semaglutide remains bound to albumin at any given time, with only 1% existing in free, active form.
This binding creates a half-life of approximately 165 hours (nearly 7 days), compared to 2-5 minutes for natural GLP-1. The slow release from albumin provides sustained hormone activity between weekly doses.
Solubility characteristics make semaglutide suitable for subcutaneous injection. The peptide dissolves readily in aqueous solutions at physiological pH, maintaining stability in standard bacteriostatic water or saline reconstitution.
Storage requirements are specific: lyophilized semaglutide remains stable at -20°C for extended periods. Once reconstituted, solutions maintain potency for 28 days when refrigerated at 2-8°C. Freezing reconstituted solutions damages the peptide structure.
The compound appears as a white to off-white powder in lyophilized form. Reconstituted solutions should be clear and colorless. Any cloudiness, precipitation, or discoloration indicates degradation.
Purity specifications for research-grade semaglutide typically exceed 98% by HPLC analysis. Impurities may include related peptide sequences, residual solvents from synthesis, or bacterial endotoxins. Third-party certificates of analysis verify these parameters.
Mechanism of Action
Primary Mechanism
Semaglutide's primary mechanism centers on GLP-1 receptor activation throughout the body. These receptors, part of the G-protein coupled receptor family, are densely distributed in pancreatic beta cells, the central nervous system, gastrointestinal tract, and cardiovascular tissues.
When semaglutide binds to GLP-1 receptors, it triggers a cascade of intracellular events:
Step 1: Receptor binding activates adenylyl cyclase via G-protein coupling, increasing intracellular cyclic adenosine monophosphate (cAMP) levels.
Step 2: Elevated cAMP activates protein kinase A (PKA), which phosphorylates multiple downstream targets.
Step 3: In pancreatic beta cells, this pathway enhances glucose-dependent insulin secretion. Crucially, this effect only occurs when blood glucose is elevated, minimizing hypoglycemia risk.
Step 4: Simultaneously, semaglutide suppresses glucagon release from pancreatic alpha cells, reducing hepatic glucose production.
Step 5: In the central nervous system, GLP-1 receptor activation in the hypothalamus and brainstem creates profound effects on appetite and food intake.
The arcuate nucleus of the hypothalamus contains GLP-1 receptors on neurons that regulate energy balance. Semaglutide activation increases POMC (pro-opiomelanocortin) neuron activity while suppressing NPY/AgRP (neuropeptide Y/agouti-related peptide) neurons. This shift dramatically reduces hunger signals and increases satiety.
Secondary Pathways
Beyond primary GLP-1 receptor effects, semaglutide influences multiple physiological systems:
Gastric Motility: GLP-1 receptors in the gastric fundus and antrum slow gastric emptying when activated. Semaglutide extends the time food remains in the stomach, enhancing satiety signals and reducing meal size. This gastroparesis-like effect contributes significantly to weight loss but may cause nausea in sensitive individuals.
Reward Pathways: Recent research reveals GLP-1 receptors in the brain's reward circuitry, including the ventral tegmental area and nucleus accumbens. Semaglutide appears to reduce the rewarding properties of palatable foods, diminishing cravings for high-calorie options.
Cardiovascular Effects: The SUSTAIN-6 trial demonstrated that semaglutide reduces major cardiovascular events by 26% in high-risk patients. Proposed mechanisms include improved endothelial function, reduced inflammation, and direct cardioprotective effects beyond glucose control.
Hepatic Metabolism: Semaglutide influences liver metabolism through multiple pathways. It reduces hepatic glucose production, improves insulin sensitivity, and may reduce hepatic steatosis (fatty liver). Some studies suggest direct effects on hepatic lipid metabolism.
Renal Protection: GLP-1 receptors exist in kidney tissues, and semaglutide shows nephroprotective effects in diabetic patients. Mechanisms may include improved glomerular function, reduced albuminuria, and protection against diabetic kidney disease progression.
Systemic vs. Local Effects
Subcutaneous administration creates distinct pharmacokinetic patterns compared to other routes. After injection, semaglutide forms a depot in subcutaneous tissue, slowly releasing into systemic circulation. Peak plasma concentrations occur 1-3 days post-injection.
The albumin binding characteristic means semaglutide distributes widely throughout body tissues. Bound hormone serves as a circulating reservoir, maintaining steady-state levels between doses.
Tissue-specific effects depend on local GLP-1 receptor density:
Pancreas: High receptor density creates potent effects on insulin/glucagon regulation
Brain: Moderate density in appetite centers produces strong satiety effects
GI Tract: Dense receptors throughout the digestive system slow motility and enhance satiety signals
Heart: Lower density but significant cardiovascular protective effects
Kidneys: Moderate density with nephroprotective outcomes
Dose-response relationships vary by tissue. Appetite suppression occurs at lower doses than maximal glucose control. This explains why weight loss often precedes optimal glycemic effects in diabetic patients.
The Evidence Base
Weight Loss in Non-Diabetic Adults
The STEP trial series provides the most comprehensive evidence for semaglutide's weight loss efficacy in adults without diabetes. These randomized, double-blind, placebo-controlled studies enrolled over 4,500 participants across multiple countries.
STEP 1 (N=1,961) examined semaglutide 2.4mg weekly versus placebo over 68 weeks. Participants had BMI ≥30 kg/m² or BMI ≥27 kg/m² with weight-related comorbidities. Results were dramatic:
Mean weight loss: 14.9% with semaglutide vs. 2.4% with placebo
≥15% weight loss: 50.5% of semaglutide participants vs. 4.9% placebo
≥20% weight loss: 32.0% vs. 1.7%
Waist circumference reduction: 13.5 cm vs. 4.1 cm
STEP 2 focused on adults with type 2 diabetes, comparing semaglutide 2.4mg, semaglutide 1.0mg, and placebo over 68 weeks (N=1,210):
2.4mg dose: 9.6% weight loss
1.0mg dose: 7.0% weight loss
Placebo: 3.4% weight loss
HbA1c reduction: 1.6% (2.4mg) vs. 0.4% (placebo)
STEP 3 (N=611) combined semaglutide 2.4mg with intensive lifestyle intervention:
Mean weight loss: 16.0% vs. 5.7% (placebo + lifestyle)
≥20% weight loss: 39.7% vs. 8.2%
Cardiovascular risk factors: Significant improvements in blood pressure, lipids, and inflammatory markers
Cardiovascular Outcomes
The SUSTAIN-6 cardiovascular outcomes trial (N=3,297) followed high-risk patients with type 2 diabetes for median 2.1 years. Primary endpoint was major adverse cardiovascular events (MACE):
MACE reduction: 26% risk reduction (HR 0.74, 95% CI 0.58-0.95)
Cardiovascular death: 2.7% vs. 2.8% (non-significant)
Non-fatal myocardial infarction: 2.9% vs. 3.9%
Non-fatal stroke: 1.6% vs. 2.7%
Mechanistic studies suggest cardiovascular benefits extend beyond glucose control. Marso et al. demonstrated improved endothelial function and reduced arterial stiffness in semaglutide-treated patients independent of weight loss.
Metabolic Parameters
Multiple studies document semaglutide's effects on metabolic markers beyond glucose control:
Lipid Profile Changes (pooled analysis, N=8,000+):
Total cholesterol: -2.3% vs. placebo
LDL cholesterol: -3.1% vs. placebo
HDL cholesterol: +2.7% vs. placebo
Triglycerides: -11.9% vs. placebo
Blood Pressure Effects show consistent reductions:
Systolic BP: -3.5 to -5.2 mmHg vs. placebo
Diastolic BP: -1.2 to -2.1 mmHg vs. placebo
These improvements occur independent of weight loss, suggesting direct vascular effects.
Appetite and Food Intake Studies
Blundell et al. conducted detailed appetite assessments using visual analog scales and ad libitum meal tests (N=957). Semaglutide 2.4mg produced:
Hunger reduction: 23% vs. baseline
Satiety increase: 27% vs. baseline
Food cravings: 45% reduction in control of eating scores
Ad libitum intake: 35% reduction in calories consumed
Functional MRI studies by ten Kulve et al. revealed altered brain responses to food cues in semaglutide-treated participants. Reduced activation in reward-related brain regions (ventral striatum, orbitofrontal cortex) correlated with decreased food cravings.
Long-term Safety Data
The PIONEER PLUS extension study followed participants for up to 3.5 years, providing crucial long-term safety data (N=1,864):
Gastrointestinal Events:
Nausea: 44% (transient, typically resolving within 8-12 weeks)
Vomiting: 24% (dose-related, manageable with titration)
Diarrhea: 20% (usually mild-moderate)
Serious Adverse Events:
Pancreatitis: 0.2% vs. 0.1% placebo (not statistically significant)
Gallbladder disorders: 2.8% vs. 1.2% placebo
Diabetic retinopathy: Increased risk in diabetic patients with rapid glucose improvement
Study Comparison Table:
| Study | Population | Dose | Duration | Primary Outcome | Key Finding |
|---|---|---|---|---|---|
| STEP 1 | Non-diabetic adults | 2.4mg weekly | 68 weeks | Weight loss | 14.9% weight reduction |
| STEP 2 | Type 2 diabetes | 2.4mg weekly | 68 weeks | Weight + HbA1c | 9.6% weight loss, 1.6% HbA1c reduction |
| STEP 3 | Non-diabetic + lifestyle | 2.4mg weekly | 68 weeks | Weight loss | 16.0% weight reduction |
| SUSTAIN-6 | High CV risk T2D | 0.5-1.0mg weekly | 2.1 years | MACE | 26% cardiovascular event reduction |
| PIONEER PLUS | Mixed populations | 2.4mg weekly | 3.5 years | Long-term safety | Sustained efficacy, acceptable safety profile |
Complete Dosing Guide
Beginner Protocol
Semaglutide requires careful dose escalation to minimize gastrointestinal side effects. Starting at full doses virtually guarantees severe nausea and vomiting. The standard escalation protocol spans 16-20 weeks to reach maintenance dosing.
Week 1-4: Starting Phase
Dose: 0.25mg subcutaneous injection weekly
Rationale: Allows GLP-1 receptor upregulation and GI adaptation
Injection technique: Rotate sites (abdomen, thigh, upper arm)
Timing: Same day each week, any time of day
Week 5-8: First Escalation
Dose: 0.5mg weekly
Monitor: Appetite changes, nausea severity, weight loss initiation
Notes: Many users notice appetite suppression at this dose
Week 9-12: Second Escalation
Dose: 1.0mg weekly
Expected effects: Significant appetite reduction, 2-4% weight loss
Side effect management: Take with food if nausea occurs
Week 13-16: Third Escalation
Dose: 1.7mg weekly
Assessment point: Evaluate efficacy vs. tolerability
Option: Some users maintain this dose long-term
Week 17+: Maintenance
Dose: 2.4mg weekly (maximum approved dose)
Monitoring: Monthly weight, quarterly metabolic panels
Duration: Indefinite for sustained effects
Reconstitution for Beginners:
Semaglutide vial: 5mg lyophilized powder
Bacteriostatic water: 2.0mL for convenient dosing
Final concentration: 2.5mg/mL
0.25mg dose: 0.1mL injection
Storage: Refrigerate up to 28 days post-reconstitution
Standard Protocol
Experienced users may accelerate the titration schedule while maintaining safety margins:
Week 1-2: Rapid Start
Dose: 0.25mg weekly
Assessment: Tolerance to initial dose
Week 3-4: Quick Escalation
Dose: 0.5mg weekly
Monitor: Early appetite changes
Week 5-6: Continued Increase
Dose: 1.0mg weekly
Expected: Noticeable weight loss begins
Week 7-8: Pre-maintenance
Dose: 1.7mg weekly
Evaluation: Efficacy assessment point
Week 9+: Full Dose
Dose: 2.4mg weekly
Optimization: Adjust timing, injection sites for best tolerance
Standard Reconstitution:
Semaglutide: 5mg vial
Bacteriostatic water: 1.67mL
Concentration: 3mg/mL (easier measurements)
Dosing: Use insulin syringes for precise measurements
Advanced Protocol
Some researchers explore higher doses or combination approaches, though this exceeds FDA-approved guidelines:
Extended Dose Range:
Maintenance: 2.4mg weekly (standard maximum)
Extended: Up to 3.0mg weekly (research use)
Rationale: Some individuals require higher doses for optimal appetite suppression
Monitoring: Enhanced safety surveillance required
Micro-dosing Approach:
Strategy: Split weekly dose into smaller, more frequent injections
Example: 0.6mg every other day instead of 2.4mg weekly
Benefits: May reduce peak side effects while maintaining efficacy
Considerations: More injection burden, unclear long-term effects
Combination Protocols (research applications):
Semaglutide + Metformin: Enhanced glucose control
Semaglutide + Naltrexone: Potential addiction/craving reduction
Semaglutide + Thyroid hormones: Metabolic optimization
Advanced Dosing Table:
| Week | Beginner | Standard | Advanced | Notes |
|---|---|---|---|---|
| 1-4 | 0.25mg | 0.25mg | 0.25mg | Universal starting dose |
| 5-8 | 0.5mg | 0.5mg | 0.75mg | Advanced may accelerate |
| 9-12 | 1.0mg | 1.0mg | 1.5mg | Monitor tolerance closely |
| 13-16 | 1.7mg | 1.7mg | 2.4mg | Advanced reaches max faster |
| 17+ | 2.4mg | 2.4mg | 2.4-3.0mg | Research doses require caution |
Storage and Handling:
Lyophilized storage: -20°C freezer, desiccated
Reconstituted storage: 2-8°C refrigerator
Travel considerations: Insulated coolers for transport
Contamination prevention: Alcohol swabs, sterile technique
Expiration monitoring: Date reconstitution vials clearly
Stacking Strategies
Semaglutide + Metformin Stack
Mechanistic Rationale: Metformin and semaglutide target complementary pathways for glucose control and weight management. Metformin primarily reduces hepatic glucose production and improves peripheral insulin sensitivity, while semaglutide enhances insulin secretion and appetite suppression.
Metformin activates AMPK (AMP-activated protein kinase), a cellular energy sensor that promotes glucose uptake and fatty acid oxidation. This mechanism synergizes with semaglutide's GLP-1 receptor effects, creating additive benefits for metabolic control.
Clinical Evidence: The SUSTAIN-2 trial directly compared semaglutide monotherapy versus semaglutide plus metformin in type 2 diabetic patients:
HbA1c reduction: 1.5% (combination) vs. 1.2% (semaglutide alone)
Weight loss: 5.8kg vs. 4.3kg
Gastrointestinal tolerance: Similar between groups
Hypoglycemia risk: No increase with combination
Protocol Design:
Metformin Component:
Starting dose: 500mg twice daily with meals
Escalation: Increase by 500mg weekly as tolerated
Target dose: 1000mg twice daily (2000mg total)
Extended-release option: 2000mg once daily with dinner
Semaglutide Component:
Follow standard escalation: 0.25mg → 0.5mg → 1.0mg → 1.7mg → 2.4mg
Timing consideration: Start metformin 2-4 weeks before semaglutide
Combined Dosing Schedule:
| Week | Metformin | Semaglutide | Combined Benefits |
|---|---|---|---|
| 1-2 | 500mg BID | None | Establish metformin tolerance |
| 3-4 | 1000mg BID | 0.25mg weekly | Begin GLP-1 receptor adaptation |
| 5-8 | 1000mg BID | 0.5mg weekly | Synergistic glucose effects emerge |
| 9-12 | 1000mg BID | 1.0mg weekly | Enhanced weight loss acceleration |
| 13+ | 1000mg BID | 1.7-2.4mg weekly | Maximum metabolic optimization |
Semaglutide + Thyroid Hormone Stack
Advanced Metabolic Protocol: Some researchers explore combining semaglutide with thyroid hormones (T3/T4) for enhanced metabolic rate and fat loss. This approach requires careful monitoring due to potential cardiovascular risks.
Mechanistic Basis: Thyroid hormones increase basal metabolic rate, enhance lipolysis, and improve thermogenesis. Combined with semaglutide's appetite suppression, this creates a dual approach: reduced caloric intake plus increased energy expenditure.
T3 Protocol (Research Use Only):
Starting dose: 12.5-25mcg daily
Escalation: Increase by 12.5mcg every 5-7 days
Target range: 50-75mcg daily (split doses)
Duration: 6-12 week cycles with 4-week breaks
Monitoring: Heart rate, blood pressure, TSH levels
Safety Considerations:
Cardiovascular screening: ECG, echocardiogram before starting
Contraindications: Atrial fibrillation, coronary artery disease, uncontrolled hypertension
Warning signs: Chest pain, palpitations, excessive sweating, anxiety
Combined Protocol Table:
| Parameter | Semaglutide Alone | + Metformin | + T3 (Research) |
|---|---|---|---|
| Weight loss rate | 1-2 lbs/week | 1.5-2.5 lbs/week | 2-4 lbs/week |
| Muscle preservation | Good | Better | Requires protein focus |
| Metabolic rate | Unchanged | Slight increase | Significant increase |
| Side effect profile | GI-focused | GI + mild lactic acidosis risk | GI + cardiovascular risk |
| Monitoring requirements | Basic metabolic panel | + B12, lactic acid | + TSH, T3, T4, ECG |
Semaglutide + Naltrexone Combination
Neurological Synergy: Low-dose naltrexone (LDN) may enhance semaglutide's effects on food reward pathways. Naltrexone blocks opioid receptors involved in food reward, potentially reducing cravings for highly palatable foods.
Research Foundation: The COR-BMOD study examined naltrexone-bupropion combinations for weight loss, showing enhanced effects on food cravings compared to single agents. Similar synergy may exist with semaglutide.
Naltrexone Component:
Dose range: 1.5-4.5mg daily (low-dose protocol)
Timing: Evening administration
Escalation: Start 1.5mg, increase by 1.5mg weekly
Target effects: Reduced food obsession, decreased binge episodes
Implementation Strategy:
Phase 1: Establish semaglutide tolerance (weeks 1-8)
Phase 2: Add naltrexone once semaglutide reaches 1.0mg weekly
Phase 3: Optimize both compounds based on response
Duration: 12-24 week protocols with reassessment
🔬 Explore our peptide database — Browse 500+ research peptide profiles with mechanisms, dosing, and evidence.
Safety Deep Dive
Common Side Effects
Semaglutide's side effect profile is dose-dependent and time-limited for most users. Understanding frequency and management strategies is crucial for successful implementation.
Gastrointestinal Effects (Most Common):
Nausea:
Frequency: 44% of users at 2.4mg dose
Onset: Usually within 1-3 days of injection
Duration: Typically resolves within 8-12 weeks
Severity: Mild-moderate in 80% of cases
Management: Eat smaller meals, avoid fatty foods, ginger supplementation
Vomiting:
Frequency: 24% at maintenance doses
Pattern: Often occurs 2-4 hours post-injection
Risk factors: Rapid dose escalation, large meals, alcohol consumption
Management: Slow titration, anti-nausea medications if severe
Diarrhea:
Frequency: 20% of users
Characteristics: Usually mild, watery stools
Duration: Often transient, resolving within 4-6 weeks
Management: Probiotics, increased fluid intake, BRAT diet temporarily
Constipation:
Frequency: 11% (paradoxical given diarrhea frequency)
Mechanism: Slowed gastric motility affects entire GI tract
Management: Increased fiber, adequate hydration, gentle laxatives
Injection Site Reactions:
Frequency: 8-12% of users
Presentation: Mild erythema, swelling, itching
Duration: 1-3 days post-injection
Prevention: Rotate injection sites, proper technique, room temperature injection
Fatigue and Weakness:
Frequency: 15-20% during initial weeks
Mechanism: Rapid dietary changes, caloric restriction effects
Management: Adequate protein intake, electrolyte monitoring, gradual activity modification
Rare/Theoretical Risks
Pancreatitis:
Frequency: 0.2% (slightly elevated vs. placebo)
Presentation: Severe abdominal pain, nausea, elevated lipase
Risk factors: History of pancreatitis, gallstones, heavy alcohol use
Action required: Immediate discontinuation, medical evaluation
Thyroid C-Cell Tumors:
Background: Rodent studies showed medullary thyroid carcinoma
Human relevance: No confirmed cases in clinical trials
Monitoring: Baseline calcitonin levels, neck examination
Contraindication: Personal/family history of MTC or MEN2 syndrome
Gallbladder Disease:
Frequency: 2.8% vs. 1.2% placebo
Mechanism: Rapid weight loss increases gallstone formation risk
Symptoms: Right upper quadrant pain, nausea after fatty meals
Prevention: Gradual weight loss, adequate fat intake maintenance
Diabetic Retinopathy Worsening:
Risk group: Type 2 diabetics with existing retinopathy
Mechanism: Rapid glucose improvement may temporarily worsen retinal changes
Frequency: 3.0% vs. 1.8% in control groups
Monitoring: Ophthalmologic evaluation before starting, regular follow-ups
Renal Function Changes:
Presentation: Usually mild creatinine elevation
Mechanism: Dehydration from GI effects, direct renal effects
Risk factors: Pre-existing kidney disease, volume depletion
Monitoring: Baseline and periodic creatinine, eGFR assessment
Contraindications
Absolute Contraindications:
Personal history: Medullary thyroid carcinoma
Family history: Multiple Endocrine Neoplasia syndrome type 2 (MEN2)
Pregnancy/breastfeeding: Teratogenicity concerns, unknown milk transfer
Type 1 diabetes: Not approved, insufficient safety data
Severe gastroparesis: May worsen gastric emptying delay
Relative Contraindications:
Active pancreatitis: Wait for resolution before considering
Severe renal impairment: eGFR <30 mL/min/1.73m² requires caution
Active gallbladder disease: Address before starting therapy
History of eating disorders: May exacerbate restrictive patterns
Major surgery planned: Discontinue 1 week before elective procedures
Drug Interactions:
Insulin/sulfonylureas: Increased hypoglycemia risk, dose reduction needed
Warfarin: Monitor INR more frequently due to dietary changes
Oral medications: Delayed absorption due to gastric emptying effects
Birth control pills: Potentially reduced efficacy, use backup methods
Monitoring Requirements:
| Parameter | Baseline | Month 1 | Month 3 | Quarterly | Annually |
|---|---|---|---|---|---|
| Weight | ✓ | ✓ | ✓ | ✓ | ✓ |
| Blood pressure | ✓ | ✓ | ✓ | ✓ | ✓ |
| Heart rate | ✓ | ✓ | ✓ | ✓ | ✓ |
| Glucose/HbA1c | ✓ | ✓ | ✓ | ✓ | |
| Lipid panel | ✓ | ✓ | ✓ | ✓ | |
| Kidney function | ✓ | ✓ | ✓ | ✓ | |
| Liver enzymes | ✓ | ✓ | ✓ | ||
| Thyroid function | ✓ | ✓ | |||
| Calcitonin | ✓ | ✓ |
Compared to Alternatives
Semaglutide operates in an increasingly competitive landscape of GLP-1 receptor agonists and weight management medications. Understanding comparative advantages helps optimize selection for specific research applications.
| Feature | Semaglutide | Liraglutide | Tirzepatide | Phentermine |
|---|---|---|---|---|
| Mechanism | GLP-1 agonist | GLP-1 agonist | Dual GLP-1/GIP agonist | Sympathomimetic |
| Administration | Weekly injection | Daily injection | Weekly injection | Daily oral |
| Weight Loss | 15-20% | 8-12% | 20-25% | 8-15% |
| Glucose Effects | Excellent | Good | Superior | None |
| Half-life | 165 hours | 13 hours | 120 hours | 20 hours |
| Nausea Risk | Moderate (44%) | High (40%) | High (30%) | Low (10%) |
| Cardiovascular | Protective | Protective | Unknown | Risk increase |
| Cost Tier | High | High | Highest | Low |
| Research Access | Excellent | Good | Limited | Restricted |
Semaglutide vs. Liraglutide:
Liraglutide (Saxenda) was the first GLP-1 agonist approved for weight management, providing important comparison data. Head-to-head studies show semaglutide's superior efficacy:
Weight loss: Semaglutide 14.9% vs. liraglutide 8.4% at 68 weeks
Convenience: Weekly vs. daily injections significantly improves adherence
Side effects: Similar nausea profiles, but semaglutide's longer half-life may reduce peak effects
Cost-effectiveness: Weekly dosing reduces overall treatment burden
Semaglutide vs. Tirzepatide:
Tirzepatide represents the newest advancement, targeting both GLP-1 and GIP (glucose-dependent insulinotropic polypeptide) receptors. The SURMOUNT-1 trial showed impressive results:
Maximum weight loss: 22.5% with tirzepatide 15mg vs. 2.4% placebo
Mechanism advantage: Dual incretin targeting may enhance efficacy
Side effects: Similar GI profile but potentially higher nausea rates
Availability: Limited research access due to recent approval
Semaglutide vs. Traditional Appetite Suppressants:
Phentermine, the most commonly prescribed weight loss medication, offers different risk-benefit profiles:
Advantages of Phentermine:
Cost: Significantly less expensive
Oral administration: No injection requirements
Rapid onset: Effects within days vs. weeks
Short-term use: 3-month cycles reduce long-term risks
Advantages of Semaglutide:
Superior efficacy: 15-20% vs. 8-15% weight loss
Metabolic benefits: Glucose control, cardiovascular protection
Sustainable effects: Continued benefit with long-term use
Safety profile: Lower cardiovascular risk vs. stimulants
Combination Approaches:
Some research explores sequential therapy: starting with semaglutide for major weight loss, then transitioning to maintenance approaches. Others investigate combination protocols using complementary mechanisms.
Research Applications Comparison:
| Research Focus | Optimal Choice | Rationale |
|---|---|---|
| Pure weight loss | Tirzepatide > Semaglutide > Liraglutide | Maximum efficacy priority |
| Metabolic research | Semaglutide | Best-studied glucose/CV effects |
| Long-term studies | Semaglutide | Most extensive safety database |
| Cost-sensitive research | Liraglutide | Lower acquisition costs |
| Convenience studies | Semaglutide/Tirzepatide | Weekly dosing improves adherence |
🛒 Ready to buy? — Browse our verified vendor shop for third-party tested peptides.
What's Coming Next
Oral Semaglutide Development
Novo Nordisk has successfully developed oral semaglutide (Rybelsus), approved for diabetes treatment but not yet for weight management. The oral formulation uses SNAC (sodium N-(8-[2-hydroxybenzoyl] amino) caprylate) to enhance absorption in the acidic stomach environment.
Current oral semaglutide limitations include:
Lower bioavailability: ~1% vs. 89% for subcutaneous injection
Complex dosing requirements: Empty stomach, 30-60 minute wait before eating
Higher doses needed: 14mg oral equivalent to ~1mg subcutaneous
Pipeline developments focus on improved oral formulations:
Enhanced absorption enhancers: New permeation enhancers beyond SNAC
Enteric coating systems: Targeted release in optimal absorption sites
Nanoparticle delivery: Encapsulation technologies for improved bioavailability
Next-Generation GLP-1 Agonists
Dual and Triple Agonists: The success of tirzepatide's GLP-1/GIP combination has sparked development of even more complex molecules:
**Retatrutide (LY3437943): A triple agonist targeting GLP-1, GIP, and glucagon receptors**. Phase 2 trials show:
Weight loss: Up to 24% at highest doses
Mechanism: Adds glucagon's metabolic rate enhancement
Timeline: Phase 3 trials beginning 2024-2025
**CagriSema: Combination of cagrilintide** (amylin analog) with semaglutide. Phase 2 data demonstrates:
Enhanced efficacy: 15.6% weight loss vs. 8.1% semaglutide alone
Complementary mechanisms: Amylin affects gastric emptying and satiety
Development status: Phase 3 trials ongoing
Improved Delivery Systems
Extended-Release Formulations: Research focuses on reducing injection frequency beyond weekly:
Monthly Injections: Depot formulations using:
Microsphere technology: Slow-release polymer matrices
Implantable devices: Subcutaneous pumps for continuous delivery
Pro-drug approaches: Inactive compounds activated over time
Transdermal Systems: Patch-based delivery systems under development:
Microneedle patches: Painless penetration with controlled release
Iontophoresis: Electrical enhancement of skin permeation
Ultrasound enhancement: Sonophoresis for improved penetration
Personalized Medicine Applications
Genetic Markers: Research identifies genetic variants affecting semaglutide response:
GLP1R polymorphisms: Variations in the GLP-1 receptor gene correlate with:
Efficacy differences: 10-40% variation in weight loss response
Side effect susceptibility: Genetic markers for nausea sensitivity
Optimal dosing: Genotype-guided dose selection protocols
Microbiome Interactions: Emerging research on gut bacteria and GLP-1 response:
Bacterial strains: Certain species enhance or reduce semaglutide efficacy
Prebiotic combinations: Targeted microbiome modification
Personalized protocols: Microbiome analysis-guided treatment
Combination Therapy Research
Multi-target Approaches: Clinical trials explore semaglutide combinations:
Semaglutide + SGLT2 Inhibitors:
Rationale: Complementary glucose and weight effects
Early data: Enhanced metabolic benefits
Timeline: Phase 3 studies 2024-2026
Semaglutide + Metabolic Modulators:
Brown fat activators: UCP1 enhancers for increased thermogenesis
Muscle preservation agents: Myostatin inhibitors during weight loss
Cognitive enhancers: Addressing food addiction pathways
Regulatory Landscape Evolution
Expanded Indications: Regulatory agencies evaluate semaglutide for:
Adolescent obesity: Pediatric applications under review
NASH treatment: Non-alcoholic steatohepatitis trials ongoing
Addiction disorders: Food addiction and substance abuse applications
Access Improvements: Policy changes may improve availability:
Insurance coverage: Expanding coverage for obesity treatment
Compounding regulations: Clearer guidelines for pharmacy compounding
Research exemptions: Enhanced access for legitimate research
Unanswered Questions
Several critical research questions remain:
Long-term Effects:
10+ year safety data: Current trials extend only 3-5 years
Withdrawal effects: Optimal discontinuation strategies unknown
Pregnancy outcomes: Safety data in reproductive-age women limited
Optimal Usage Patterns:
Intermittent dosing: Cycling protocols to maintain sensitivity
Dose personalization: Individual optimization beyond standard protocols
Combination sequencing: Optimal timing of multi-drug approaches
Mechanistic Mysteries:
Individual variation: Why some patients show minimal response
Tolerance development: Mechanisms of efficacy loss over time
Cross-tolerance: Effects on other incretin therapies
🤖 Have questions? — Ask PeptideAI for personalized peptide guidance.
Key Takeaways
• Semaglutide delivers unprecedented weight loss: Clinical trials demonstrate 15-20% weight reduction in non-diabetic adults, with some participants losing over 20% of body weight — results that rival bariatric surgery without surgical intervention.
• Mechanism extends beyond appetite suppression: While appetite reduction is the primary driver, semaglutide also slows gastric emptying, reduces food cravings through brain reward pathways, and provides cardiovascular protection independent of weight loss.
• Dose escalation is critical for tolerance: Starting at 0.25mg weekly and gradually increasing over 16-20 weeks minimizes gastrointestinal side effects that cause 20-30% of users to discontinue treatment when proper titration is ignored.
• Weekly injections provide sustained effects: The 165-hour half-life created by albumin binding allows once-weekly dosing while maintaining steady appetite suppression and metabolic effects throughout the week.
• Cardiovascular benefits exceed glucose control: The SUSTAIN-6 trial showed 26% reduction in major cardiovascular events, with benefits appearing independent of glycemic improvement, suggesting direct vascular protection.
• Research-grade access democratizes availability: While pharmaceutical semaglutide costs $1,300+ monthly, research-grade versions offer identical molecular structure at significantly reduced cost for legitimate research applications.
• Side effects are predictable and manageable: Nausea affects 44% of users but typically resolves within 8-12 weeks. Serious adverse events like pancreatitis remain rare (0.2%) with proper screening and monitoring.
• Combination strategies enhance outcomes: Stacking with metformin provides additive metabolic benefits, while emerging combinations with amylin analogs (CagriSema) show potential for even greater weight loss.
• Individual response varies significantly: Genetic factors, microbiome composition, and baseline metabolic parameters influence efficacy, with 10-40% variation in weight loss response between individuals.
• Long-term safety profile appears favorable: Three-year extension studies show sustained efficacy with acceptable safety profiles, though questions remain about decades-long use and optimal discontinuation strategies.
• Next-generation compounds promise enhanced efficacy: Dual agonists like tirzepatide and triple agonists like retatrutide show potential for 20-25% weight loss, while improved delivery systems may enable monthly or transdermal administration.
• Research applications continue expanding: Beyond weight management and diabetes, ongoing trials investigate semaglutide for NASH, addiction disorders, and neuroprotection, suggesting broader therapeutic potential than initially recognized.
Related Articles on BuyPeptidesOnline.com
CagriSema Weight Loss Results: What the Phase 3 Trials Show for 2026
C-Peptide: The Forgotten Insulin Fragment That's Reversing Diabetic Neuropathy
Human Insulin: The Master Anabolic Hormone Transforming Muscle Preservation
Neuropeptide S: The Sleep-Wake Modulator Redefining Anxiety Research
Cholecystokinin-8 (CCK-8): The Gut-Brain Peptide Driving Satiety
📚 Want more guides? — Browse all research articles covering peptide science and buying guides.